
Check for emergency symptoms first. Get emergency care now for new difficulty passing or controlling urine, new loss of bowel control or sensation, numbness around the genitals or anus, or new sciatic pain down both legs. Severe or worsening weakness or numbness in both legs also needs emergency care. Pain location, walking and certain movements can give clues. The patterns below cannot diagnose the cause without an assessment.
“Expert Review: This article includes clinical insights from Dr. Vivek Arora, a physical therapist (physiotherapist) with 20+ years of experience.”
Few things confuse smart, capable people quite like trying to point to where their pain “really” is. You feel an ache that wraps around the side, the groin, the buttock, maybe down the thigh — and the honest answer to “is this my back or my hip?” is often “I genuinely can’t tell.” That uncertainty matters more than it seems, because the wrong assumption sends you toward the wrong stretches, the wrong reassurance, and sometimes months of effort aimed at the wrong joint.
Lower back or hip pain often requires a history and examination because the symptom areas overlap. Observations can help you describe the problem, but they cannot reliably separate the structures at home or replace assessment when symptoms are severe or persistent.
Key Takeaways
- Location is the first clue, not the last word. True hip-joint pain classically shows up in the groin and front of the thigh; mechanical back pain tends to sit across the lower spine and buttock.
- Trunk and leg movements can affect both regions. Their response is useful history rather than a reliable source-identification test.
- Hip and spinal conditions can both refer pain below the knee. The point where pain stops cannot reliably separate them.
- Treatment and prognosis depend on the cause. Imaging is selected for a clinical question rather than ordered for every painful region.
- A few red flags genuinely warrant prompt assessment — and they are the same whether the source is back or hip.
Why your back and hip get confused in the first place
The lower back and the hip are neighbors that share the wiring. The lumbar spine houses nerve roots that travel down into the leg, the hip joint sits just below and in front of the pelvis, and the sacroiliac (SI) joint — the connection between the spine’s base and the pelvis — sits squarely between the two. Layer in muscles like the glutes, hip flexors, and deep rotators that cross both regions, and you have an anatomy almost designed to produce mixed signals.
This is why a hip problem can masquerade as back pain and a spine problem can masquerade as hip pain. Clinically, the overlap is well recognized: people with combined hip and lumbar issues commonly report low back pain together with buttock, groin, thigh, and sometimes knee pain, and the shared symptoms can delay an accurate read of which structure is the main driver. The body doesn’t hand you a labeled diagram. It hands you a region that aches.
Referred pain means discomfort is felt away from its source. Hip and spinal conditions can also coexist and influence movement, but a flare when the back feels stiff does not prove that one joint is compensating for the other.
Is it your back or your hip? Start with where it actually hurts

Groin pain can prompt consideration of the hip, while back or buttock pain can prompt a spinal, SI or other assessment. None of these locations is a single reliable filter, and more than one condition can be present.
The hip joint is deep within the pelvis, while people often use “hip” to mean the outer side. Pointing to the exact area helps communication, but side pain does not exclude joint disease or establish an SI or lumbar cause.
Locations to describe:
- Groin or front of the thigh: hip and other pelvic or spinal causes may be considered.
- Belt-line or beside the spine: several back and other conditions are possible.
- One dimple or the back of the pelvis: location alone cannot identify the SI joint.
- Outer hip tenderness or pain lying on that side: local soft tissues may be involved, but examination is needed.
What does back-origin pain feel like versus hip-origin pain?
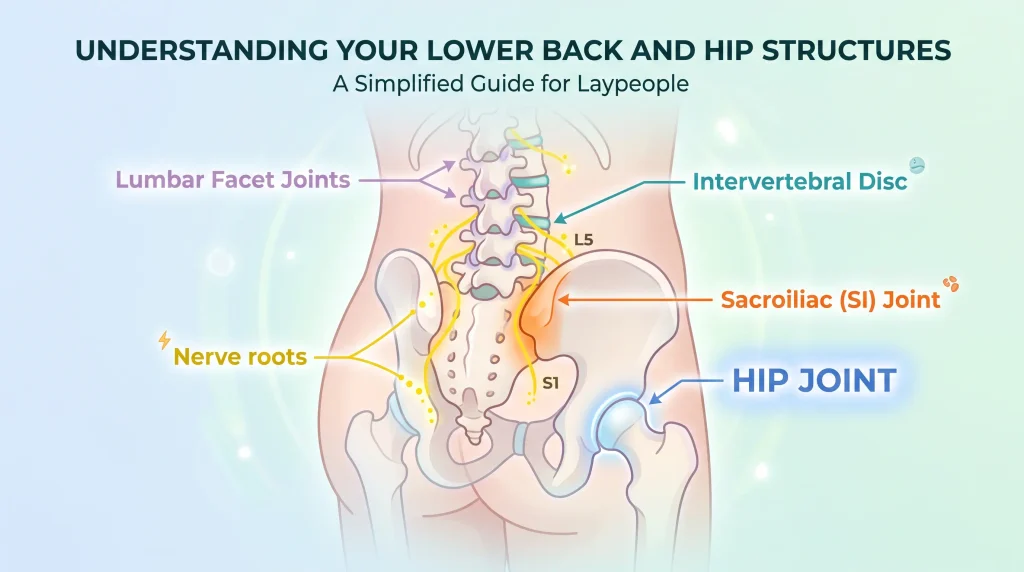
Bending, sitting, squatting, pivoting or putting on socks can affect symptoms in overlapping conditions. The movement that hurts does not reliably identify the structure doing the hurting.
A few patterns from real practice make this concrete. Hip-joint pain often produces a deep, hard-to-pinpoint ache that people instinctively cup with a C-shaped hand around the groin and side — clinicians call it the “C sign.” It tends to bother you when the joint is loaded and rotated: pivoting in the kitchen, climbing stairs, or that awkward twist to reach the back seat. Putting on shoes and socks becomes a small daily battle because deep hip flexion is exactly what an irritated joint dislikes.
Spinal nerve-root pain may travel into the leg with altered sensation or weakness, but back pain can also refer without nerve involvement. Hip-joint pain can extend below the knee. See the guide to symptoms that can accompany sciatica; coughing or sneezing alone cannot diagnose the source.
Symptom-pattern table: back vs hip vs SI joint
| Observation | Possible relevance | Limitation |
|---|---|---|
| Groin or front-thigh pain | May prompt hip assessment | Spinal, pelvic and other causes can overlap |
| Back or buttock pain | May prompt spinal, hip or SI assessment | Location alone cannot diagnose a structure |
| Pain below the knee | Can occur with hip or spinal disease | Its end point is not a reliable home test |
| Tingling, numbness or weakness | May involve a nerve or another condition | Examination and urgency depend on the full findings |
| Pain with pivoting, bending or stairs | Shows a task that is difficult | Does not establish which joint is responsible |
Use the table to describe symptoms. It cannot assign a diagnosis or determine a rehabilitation programme.
What about pain that spreads down the leg?
The end point of leg pain is not a dependable separator. Hip osteoarthritis can refer below the knee, while spinal referred pain may remain in the thigh. In one study of patients awaiting hip replacement, 47% reported pain below the knee; that selected sample is an illustration of overlap, not a rate for all hip pain (Khan et al.).
New or worsening weakness or foot drop needs urgent assessment, whether the cause is spinal or peripheral.
When is a red flag actually a red flag?
Many back and hip presentations are manageable without surgery, but symptoms can also indicate fracture, infection, neurological disease or another cause. Do not use a likely location to dismiss warning signs.
Use these care pathways:
- Get emergency care now for new difficulty passing or controlling urine, loss of bowel control or sensation, or numbness around the genitals or anus.
- New or worsening weakness in one leg needs urgent medical assessment. New bilateral sciatic pain or severe or worsening weakness or numbness in both legs needs emergency care.
- Severe hip pain after a fall or injury, or inability to walk or bear weight, needs emergency assessment. Serious-accident back pain also needs emergency care.
- A hot or swollen hip, fever or feeling unwell needs urgent medical advice. Persistent night pain, unexplained weight loss or a cancer history warrants assessment.
- Age alone does not make pain an emergency, but it informs the assessment alongside the symptoms and medical history.
None of these are about back versus hip. They’re about ruling out the uncommon-but-serious, and they apply to both.
When do you actually need a scan?
Imaging decisions differ for back and hip conditions. Routine early spinal imaging is discouraged for uncomplicated low back pain; a suspected hip fracture or other urgent condition follows a different pathway. An examination guides whether an X-ray, MRI or another test is needed.
Imaging findings must fit the clinical picture. A diagnostic injection can sometimes contribute to a specialist assessment, but relief is not an infallible proof of the single pain source. The plain-language imaging guide discusses common report limitations.
Myths that send people down the wrong path
“Pain on the side cannot be the hip joint.” Location overlaps. “A scan always identifies the painful tissue.” It may show relevant or incidental findings. “I must rest until all pain disappears.” For uncomplicated symptoms, manageable activity is often reasonable, but suspected fracture or infection needs assessment first.
Some exercise principles overlap, but the right plan depends on the condition. Arthritis, fracture, nerve symptoms and tendon pain do not all follow the same progression.
From the Clinic: Dr. Arora’s Expert Insight
Pointing to pain is useful for communication. It does not allow a clinician to identify the source in ten seconds; the history, examination and relevant tests must be interpreted together.
Hip and back conditions may coexist. An assessment should consider both without presuming that a stiff hip caused the back problem or that a particular strengthening exercise cannot help because of its label.
Notice which tasks change symptoms, how far pain spreads and whether strength or sensation changes. Bring those observations to an assessment rather than using trunk-versus-leg movement as a home diagnosis.
What should you do in the first few days?
If there are no warning signs and symptoms are manageable, try comfortable activity, position changes and temporary modification of clearly aggravating tasks. Do not start a walking programme instead of assessment if you cannot bear weight, have a hot swollen hip or have new neurological findings.
🩺 What to do today (next 24–72 hours)
- Try brief comfortable activity if you can bear weight safely; walking is optional and should not be forced through worsening symptoms.
- Find two or three comfortable positions and use them deliberately when pain rises, rather than freezing in the painful one.
- Temporarily drop the clear aggravator — the deep squat, the long uninterrupted drive, the twist you already know hurts — without bubble-wrapping your whole day.
- Heat or cold is optional for comfort. Protect the skin, stop if uncomfortable and avoid sleeping with a pack. The heat and ice guide discusses evidence and safety.
- Note your provocateurs. Write down which movements spike it; that record is worth more than guessing later.
Quick check: what should you describe?
Answer yes or no:
- Which trunk movements or sitting positions change symptoms?
- Which leg movements or weight-bearing tasks are difficult?
- Where is the deepest ache, and are there pelvic or abdominal symptoms?
- Does pain spread below the knee, with or without tingling or numbness?
- Have strength, balance or the ability to bear weight changed?
These observations are not a score. They help an examination without assigning a back, hip or SI diagnosis.
How rehab progresses once the flare settles
An individualized plan can build movement and strength toward your goals. Symptoms, function, medical findings and the response over time all matter; a fixed phase sequence is not necessary for every condition.
| Goal | Example approach | Review |
|---|---|---|
| Manage symptoms | Comfortable activity and appropriate task modification | Exclude warning signs first |
| Improve movement | Selected mobility or task practice | Diagnosis, comfort and function |
| Build capacity | Individualized strength and activity progression | Response during and after activity |
| Return to demands | Gradual work or recreation practice | Relevant clinical restrictions and goals |
Mobility, strengthening, activity modification or other treatment is selected for the actual findings. Neither pain location nor a home checklist selects a hip or trunk exercise. The physical therapy exercise guide offers examples to discuss.
Do’s and don’ts specific to this problem
Do: Record helpful observations, maintain manageable activity when safe and seek assessment if symptoms persist or worsen. Walking can aggravate some hip, nerve or vascular conditions and is not obligatory.
Do not: Diagnose the source from side-of-pelvis pain or repeatedly force a provoking movement. Exercise timing and return to a task should reflect the cause and response, not a compulsory one-week pause.
When does conservative care stop being enough?
Seek review if symptoms worsen, limit ordinary activity or do not improve after a few weeks; earlier assessment may be appropriate for substantial pain. A scan or injection is considered when it could help a clinical decision rather than automatically after “failed” rehabilitation.
Specialist or surgical care depends on the diagnosis and goals. Severe hip arthritis may justify a joint-replacement discussion, while neurological emergencies, fracture or infection need their own pathways. Do not wait for exercise to fail when urgent warning signs are present.
Conclusion
Lower back or hip pain can overlap in location and response to movement. Groin pain, a painful pivot or pain below the knee are useful observations, but none reliably separates back, hip and SI-joint causes at home.
Choose manageable activity when appropriate, watch for warning signs and obtain assessment if the cause is unclear or symptoms persist, worsen or limit daily life. An individualized plan follows the findings rather than a symptom-map label.
Related reading: when right-sided back pain in women needs a medical assessment.
Related reading: how sciatica and knee pain can overlap.
Frequently Asked Questions
1. How can I tell if my pain is from my back or my hip at home?
You can describe the location, triggers and any leg symptoms, but you cannot reliably determine the source from these observations alone. Hip disease can refer below the knee and spinal pain can remain in the buttock or thigh. An assessment considers both.
2. Can hip problems cause lower back pain?
Hip and back problems can coexist, and hip disease may produce referred pain in the buttock or nearby regions. A painful or stiff hip does not prove that compensatory loading caused the back pain; assessment helps identify relevant contributors.
3. Why does my pain go down my leg?
Hip disease, spinal referred pain, nerve conditions and other causes can produce leg pain. Crossing the knee does not diagnose sciatica. New or worsening weakness needs urgent assessment, with emergency care for the neurological warning signs above.
4. Do I need an MRI to find out which one it is?
Not always. A clinician selects imaging according to the suspected cause and whether the result will change care. Suspected hip fracture or other urgent findings need prompt evaluation rather than a blanket delay in imaging.
5. Is it safe to exercise if I can’t tell where the pain is coming from?
Manageable activity may be reasonable for uncomplicated symptoms, but do not exercise through inability to bear weight, a hot swollen hip, fever, new weakness or another warning sign. Persistent uncertainty or worsening symptoms justifies assessment.
6. Will this become a permanent problem?
The outlook depends on the cause. Many episodes improve, while some conditions need ongoing care. Persistent or worsening symptoms deserve review rather than a promise of recovery or an assumption that the problem is permanent.
7. When should I see someone urgently rather than wait it out?
Get emergency care now for new difficulty passing or controlling urine, loss of bowel control or sensation, or numbness around the genitals or anus. New sciatic pain down both legs or severe or worsening weakness or numbness in both legs also needs emergency care. Get urgent medical assessment for new or worsening weakness in one leg. Get emergency care after a serious accident. Seek medical assessment for persistent night pain, fever or unexplained weight loss.
Medical Disclaimer
This article is for general education and is not a substitute for individualized medical care. It cannot diagnose your specific condition or replace a hands-on assessment by a qualified clinician. If your symptoms are severe, worsening, or accompanied by any of the red-flag features described above, arrange a professional evaluation. Always seek personalized guidance before starting or changing an exercise or treatment program.
References
- Buckland AJ, Miyamoto R, Patel RD, Slover J, Razi AE. Differentiating Hip Pathology From Lumbar Spine Pathology: Key Points of Evaluation and Management. J Am Acad Orthop Surg. 2017 Feb;25(2):e23–e34. doi:10.5435/JAAOS-D-15-00740. https://pubmed.ncbi.nlm.nih.gov/28045713/
- Khan AM, et al. Hip osteoarthritis: where is the pain? Ann R Coll Surg Engl. 2004;86(2):119–121.
- NHS. Hip pain in adults. Assessment and urgent warning signs.
- National Institute for Health and Care Excellence. Low back pain and sciatica in over 16s: assessment and management (NG59). Recommendations on assessment, imaging and management.



