
Expert Review: This article includes clinical insights from Dr. Vivek Arora, a physical therapist (physiotherapist) with 20+ years of experience.
If you are stuck deciding between chiropractor vs massage for lower back pain, you are already asking a reasonable question — but most people stop one step too early. Both can feel excellent. Both can genuinely reduce pain. And both can still leave you exactly where you started a week later.
There is no reliable symptom-based rule that makes chiropractic manipulation better for a ‘stuck’ back or massage better for a ‘tight’ back. Both are forms of manual care that may offer short-term comfort for selected patients. NICE recommends considering manual therapy only as part of a treatment package that includes exercise, not as a stand-alone fix.
Key takeaways
- Neither is a cure, and both are legitimate tools. The useful question is not which one wins, but which one calms your symptoms enough to let you start loading the back again.
- Match the tool to the symptom pattern. Guarded, stress-linked tightness responds better to massage. A back that feels stuck and catches on specific movements responds better to manipulation.
- Relief fades because demand still exceeds capacity. If your sitting hours, lifting habits and bending strategy do not change, the same tissue gets irritated again.
- Set a trial length before you book. Two to four sessions with a measurable functional goal is a fair test. Open-ended maintenance packages rarely are.
- Leg symptoms change the plan. Pain below the knee, numbness or weakness needs assessment rather than a choice between two hands-on treatments.
Why does the relief keep wearing off?
Because passive treatment changes how the back feels, not how much it can tolerate. Think of your spine as having a credit limit. Demand is what you ask of it: sitting hours, lifting volume, stress, poor sleep. Capacity is what it can absorb: mobility, strength, endurance, coordination. A session lowers symptoms for a while. If demand still outstrips capacity, the same tissues get irritated again.
It also helps to remember that low back pain is a symptom, not a diagnosis. Two people describing identical pain can have completely different drivers:
- Mechanical overload — a sudden spike in sitting, lifting or activity
- Muscle guarding — the nervous system stiffening the area to protect it
- Joint irritation — facet joints, the sacroiliac region, the thoracolumbar junction
- Disc sensitivity — usually sensitized tissue rather than a dramatic slip
- Nerve irritation — sciatic-type referral, tingling, numbness
- Deconditioning — low endurance, so ordinary loads start to feel threatening
The three things that reliably close the relief window
1. The nervous system has learned the pattern. After repeated flares, ordinary inputs — sitting, bending, a stressful week — start producing outsized pain. Hands-on treatment quiets that temporarily; only graded exposure teaches the system that the movement is safe.
2. The movement strategy keeps poking the same tissue. Bending mostly from the low back rather than the hips, ribs flared with a locked pelvis, knees locked and glutes offline, breath held through every effort. A session cannot outrun a hundred repetitions a day.
3. What looks like core weakness is usually an endurance gap. Plenty of strong people cannot hold a neutral position without fatiguing, cannot brace briefly for a lift and then relax again for walking, and end up either rigid and sore or collapsed into a slump. Neither state is comfortable for long.
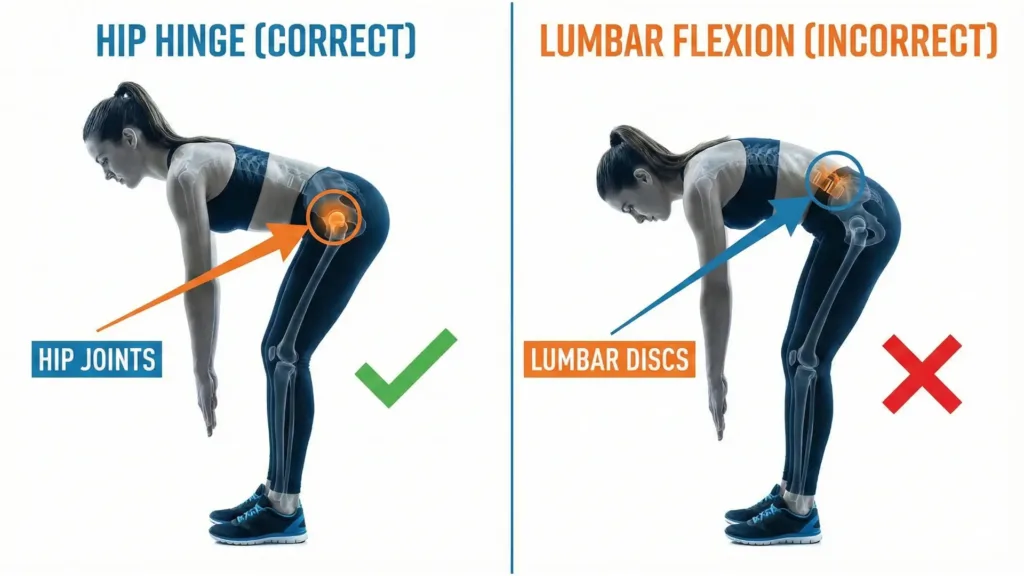
There is a fourth possibility worth naming: the back may not be the main driver at all. Hip stiffness, a stiff mid-back, altered gait and even limited ankle mobility change how load reaches the lumbar spine. Treat only the sore area and you get a relief window while the driver carries on untouched.
Chiropractor vs massage for lower back pain: what does each one actually change?
Massage and spinal manipulation may influence comfort, perceived stiffness and pain, but their effects do not prove that a muscle was tight or a spinal joint was misaligned. Neither treatment has been shown to permanently realign the spine or identify the specific tissue responsible for back pain.
Massage therapy: tone, circulation and threat level
Massage can help some people feel more comfortable in the short term, but changes in muscle tone or circulation are not established diagnostic explanations for its effect. The strongest practical aim is to use any relief to support activity rather than depending on repeated passive treatment.
Most likely to help when
- The pain is a diffuse ache rather than a sharp catch
- You feel locked up after long sitting or a stressful stretch of weeks
- Flare-ups ease once you start moving
- You leave sessions calmer and looser, not bruised for days
Usually not enough on its own when
- Bending reliably triggers pain, which points to a direction-specific problem
- Lifting keeps causing flares, which points to a load tolerance problem
- You have leg symptoms — tingling, numbness or shooting pain
- You need the same reset every single week
Spinal manipulation: joint motion and pain modulation
Spinal manipulative therapy is not about bones being out of place. It is a combination of mechanical change at a stiff segment and a neurological effect on pain. It can reduce pain quickly, improve motion where a segment feels blocked, and restore movement confidence — which matters more than it sounds when fear has been limiting activity.
The honest version of the evidence is modest. A systematic review and meta-analysis of randomized trials found that manipulation produced effects on pain similar to other recommended therapies, and a small improvement in function, with adverse events that were mostly musculoskeletal, transient and mild to moderate. That is a useful tool with a real but limited ceiling — not a reason to book twenty sessions.
Most likely to help when
- The back feels mechanically stuck rather than simply sore
- You have a fresh flare and need symptoms down far enough to start rehab
- Certain positions clearly worsen it and others clearly ease it
- Manual testing reproduces your symptoms and then reduces them
Not the main answer when
- There is significant osteoporosis or fracture risk, or any suspicion of infection or cancer
- Neurological signs are progressing — worsening weakness, foot drop
- Relief lasts hours and nothing about your daily triggers has changed
- The pain is primarily driven by overload and poor endurance
How do I decide which one to try first?
Related guidance: a structured home-exercise program; warning signs after spinal manipulation. These links provide background information, not a diagnosis.
Choose an appropriate clinician and treatment after considering your medical history, symptoms, preferences, treatment risks and ability to remain active. Pain that feels ‘stuck’ is not an indication for spinal manipulation, and symptoms that suggest neurological compromise require assessment before manual treatment.
| Your situation | Massage | Manipulation | Broader management to consider |
|---|---|---|---|
| Stress-linked flare, general tightness, poor sleep | Optional short-term relief when appropriate | May help selected patients | Comfortable movement and self-management |
| Stiff, stuck back after travel or a long sitting stretch | Optional short-term relief when appropriate | Optional short-term relief when appropriate | Mobility, endurance and dosing your sitting time |
| Acute flare after an awkward bend or lift | May help selected patients | Optional short-term relief when appropriate | Gradual return to comfortable activity |
| Chronic pain recurring every few weeks | Short-term relief possible | Short-term relief possible | A structured exercise plan and changed daily habits |
| Sciatica-like symptoms below the knee | Secondary role at best | Requires medical screening and individualized advice | Neurological assessment, activity and graded rehabilitation |
If your pain travels below the knee or comes with tingling, do not guess between the two. Nerve-related symptoms need irritability management, graded exposure and progressive loading. Massage may calm the surrounding tension and manipulation helps some cases, but neither substitutes for a structured plan and a proper neurological screen.
Questions worth asking before you pay
- On cost: “How many sessions before I should notice a meaningful change in function?” and “What is the plan if I only improve temporarily?” If the answer is to keep coming indefinitely, that is your answer.
- On safety: “What would make you refer me out?” and “How will you screen me for neurological change?” Any good practitioner, of either kind, welcomes both questions.
- On value: put part of the budget into a short block of exercise programming, so the relief window converts into durable capacity instead of a repeat booking.
When is hands-on treatment the wrong call entirely?
A small proportion of back pain is not mechanical, and no amount of manual therapy is appropriate until it has been ruled out. The features below each point toward something that changes the plan, so they warrant assessment rather than a booking.
Emergency assessment now
- New bladder or bowel control problems, or numbness around the groin and inner thighs. This combination may indicate cauda equina compression, where the delay before treatment strongly influences recovery.
- Rapidly worsening leg weakness or foot drop. Progressive motor loss suggests a nerve root under sustained pressure, and monitoring it at home is not a safe option.
- Fever, chills or unexplained weight loss alongside severe back pain. These raise the possibility of spinal infection or systemic disease rather than a joint or muscle problem.
- Significant trauma such as a fall or a crash, particularly over age 50 or with low bone density. Fracture needs to be excluded before anyone applies force to the spine.
- A history of cancer or immune suppression with new severe pain. The threshold for imaging is deliberately lower in this group.
- Severe constant pain that does not change with position, especially at night. Mechanical pain almost always responds to a change in posture; pain that ignores position needs explaining.
Assessment within days
- Sciatica that is worsening week by week. A stable pattern can be managed conservatively; an escalating one needs review before it becomes a motor problem.
- Numbness that is expanding or persistent. Spreading sensory change suggests the nerve involvement is increasing rather than settling.
- Severe pain with an inability to stand upright. A fixed lateral or forward-leaning posture usually reflects strong protective spasm and often responds better to guided treatment than to guesswork.
From the Clinic: Dr. Arora’s Expert Insight
The pattern I see most often is this: someone has a genuinely good session, walks out feeling loose, and returns to the same eight to ten hours of sitting and the same bending strategy that produced the flare. When pain comes back, they conclude the treatment failed and go looking for another reset — without ever rebuilding capacity in between.
The piece almost nobody evaluates is the practitioner rather than the profession. The title on the door guarantees nothing about technique selection, red-flag screening, or the willingness to say “this is not the right treatment for you.” Social media has made this worse, because a dramatic clip of a spine being manipulated looks like a cure in eight seconds. Real recovery is slower and duller: short-term symptom relief paired with the right rehab and smarter load management.
What actually fixes it: the relief-then-rebuild plan
Active rehabilitation is the part that changes capacity. A Cochrane review found moderate-certainty evidence that exercise is probably effective for chronic low back pain compared with no treatment, usual care or placebo, though gains in function were modest. Modest and durable beats dramatic and temporary. The sequence below is what that looks like week by week.
Step 1: The seven-day flare protocol
Do this for three to seven days:
- Walk 10–20 minutes daily, split into shorter bouts if needed
- Break up static positions every 30–45 minutes
- Use heat or cold only if it genuinely helps you — a comfort tool, not a treatment
- Protect sleep: side-lying with a pillow between the knees, or on your back with the knees supported
Avoid: stretching aggressively into sharp pain, heavy lifting during a hot flare, and full bed rest, which usually increases stiffness rather than reducing it.
Step 2: Fix the hinge
If bending triggers your pain, hip hinge practice is the single most transferable skill you can build — it is what removes the repeated flexion load from the lumbar spine during every bend, lift and reach of the day.
- Stand 15–20 cm (6–8 in) from a wall, feet hip-width apart.
- Keep the ribs down and soften the knees.
- Push the hips back until your buttocks tap the wall.
- Keep the spine long, and feel it in the glutes and hamstrings rather than the low back.
Dose: 2 sets of 8–10 reps daily for a week.
Step 3: Build trunk endurance
Pick two of the three below. The target is calm control, not shaking through pain — these are endurance exercises, and endurance is exactly the quality that was missing.
- Modified side plank (knees down): elbow under shoulder, straight line from shoulder to knee. 3 holds of 10–20 seconds per side, 4–5 days a week.
- Dead bug, performed slowly: brace gently, as if tightening a belt one notch, then lower the opposite arm and leg without arching. 2 sets of 6–8 per side, 4–5 days a week.
- Bird dog, quality over height: extend the opposite arm and leg to trunk level without rotating the pelvis. 2 sets of 6 per side, 4–5 days a week.
Step 4: Add hip and leg strength
Stronger hips mean the spine contributes less to every lift, and this is usually where the durable change comes from.
- Glute bridge progression: double-leg, then marching, then single-leg. 2–3 sets of 8–12, three days a week.
- Split squat, short range first: short stance, tall torso, knee tracking over the mid-foot. 2 sets of 6–10 per side, 2–3 days a week.
Step 5: Return to lifting
Three rules cover most of it: keep the load close to your body, hinge before you bend, and set the brace before you lift rather than during it. This is the step that prevents the familiar sequence of feeling great after a session, lifting something awkward, and flaring again by the evening.
Step 6: Use hands-on care strategically
- Use massage when you are guarded and need the system to downshift
- Use manipulation when you are stiff and need enough symptom relief to move
- Always attach the plan: 10–15 minutes of daily movement plus two or three strength sessions a week
Do’s and don’ts that prevent recurrence

Do
- Take micro-breaks — 60 seconds of walking every 30–45 minutes of sitting
- Increase activity in weekly steps rather than in random spikes
- Track your actual triggers: sitting time, lifting volume, daily steps, flare timing
Don’t
- Chase perfect alignment — it is not a measurable or achievable target
- Stretch hard into tingling or shooting nerve pain
- Avoid movement out of fear, which tends to increase guarding
- Change five variables at once — change one, then measure the response
Myths vs facts
Myth: “If massage helps, muscles are the root cause.”
Fact: Massage can reduce guarding even when the actual driver is movement strategy or a sensitized nervous system. Response to a treatment does not identify the cause.
Myth: “If an adjustment helps, my spine was out of place.”
Fact: Relief usually reflects pain modulation and improved motion tolerance rather than a bone being repositioned.
Myth: “I will need maintenance forever.”
Fact: Most people reduce their reliance on passive care substantially once capacity improves and the daily triggers change.
The bottom line
Neither manipulation nor massage is a proven long-term solution on its own. If a qualified clinician considers manual treatment appropriate, combine it with exercise and self-management and review meaningful outcomes such as walking, sleep and return to activity. Seek prompt assessment for new weakness, spreading neurological symptoms or other warning signs.
FAQ
Which is better for an acute flare-up?
Neither manipulation nor massage consistently wins based on whether the back feels ‘stuck’ or ‘tight’. Both may provide short-term symptom relief, and exercise and self-management remain important.
How many sessions should I try before deciding?
There is no universal number of sessions to try. Agree on a functional goal, assess whether treatment helps and reconsider the approach if progress is lacking.
Can deep tissue massage make things worse?
Deep pressure can aggravate some symptoms or cause soreness. Reduce intensity or stop if treatment repeatedly worsens pain, causes significant bruising or produces neurological symptoms.
Is spinal manipulation safe for the lower back?
Transient soreness is relatively common after spinal manipulation. Serious complications are rare but possible, and risk depends on medical conditions and proper screening. New weakness or bladder/bowel changes need urgent assessment.
What should I do if pain shoots down my leg?
New or worsening pain down a leg, numbness or weakness warrants assessment. Gentle activity may be appropriate if comfortable, but neither manual treatment automatically addresses a nerve problem.
Why do I feel great after a session but worse the next morning?
A flare after a session can reflect several possibilities, including temporary treatment effects, the underlying condition or another problem. Avoid assuming the patient’s sitting or lifting habits caused it.
Does an adjustment have to crack to work?
No. The audible pop comes from gas released within the joint and does not predict the result. Improved movement and reduced symptoms are the only outcomes worth measuring.
Should I stop exercising if exercise triggers pain?
Comfortable exercise can often continue with adjustments, but increasing neurological symptoms, severe pain or other warning signs are reasons to stop and seek assessment.
Medical disclaimer
This article is general education and cannot replace an individual assessment. Choosing between hands-on treatments is a clinical decision that depends on your examination findings, and any severe, persistent or neurological symptom should be evaluated in person by a qualified clinician.
References
- Rubinstein SM, de Zoete A, van Middelkoop M, Assendelft WJJ, de Boer MR, van Tulder MW. Benefits and harms of spinal manipulative therapy for the treatment of chronic low back pain: systematic review and meta-analysis of randomised controlled trials. BMJ. 2019;364:l689.
- Hayden JA, Ellis J, Ogilvie R, Malmivaara A, van Tulder MW. Exercise therapy for chronic low back pain. Cochrane Database of Systematic Reviews. 2021;9:CD009790.



