
Check for emergency symptoms first. Get emergency care now for new difficulty passing or controlling urine, new loss of bowel control or sensation, numbness around the genitals or anus, or new sciatic pain down both legs. Severe or worsening weakness or numbness in both legs also needs emergency care.
Imagine standing after a long meeting and feeling an unexpected ache across your lower back. Understanding possible contributors and warning signs can guide sensible next steps, but a single article cannot diagnose every cause or guarantee that a flare will not recur.
Many episodes of lower-back pain are nonspecific, meaning there is no single structure that can be confidently identified as the source. Activity, sleep, stress and medical factors can influence symptoms. Serious conditions are less common, but warning signs and clinical assessment still matter, including when symptoms are unusual or progressively worsening.
The practical consequence is encouraging: when you reduce the load for a short period and then rebuild capacity, episodes become less frequent and less intense. That is the whole plan in one sentence, and the rest of this guide is about how to apply it to your particular pattern.
Key takeaways
- Irritation is not damage. Most flares reflect tissues that are sensitized and healable rather than structurally injured, which is why the pain can be severe and still resolve.
- Causes stack rather than stand alone. A bad night’s sleep, a long drive and one awkward lift in the same week will do what none of them does on its own.
- Lower the load first, then raise capacity. Short-term modification buys relief; four to eight weeks of graded strength work is what stops the pattern repeating.
- Scans rarely change the first few weeks. Without red flags, imaging mostly finds age-related changes that are also present in people with no pain at all.
- Get emergency care now for new difficulty passing or controlling urine, loss of bowel control or sensation, or numbness around the genitals or anus. New sciatic pain down both legs or severe or worsening weakness or numbness in both legs also needs emergency care. Get urgent medical assessment for new or worsening weakness in one leg. Arrange medical review for unexplained weight loss. Back pain with fever or feeling very unwell needs urgent advice.
Why does my lower back suddenly hurt for no reason?
Pain that appears “out of nowhere” is usually the end of a slow accumulation rather than a single event. Sleep debt, a stressful stretch at work, several days of unusually long sitting and one rushed lift each shave a little off your tolerance. The bend that finally hurts is not the cause; it is simply the moment the margin ran out.
Think of your back like a well-trained team. On good days there is plenty of headroom between the weight of your day and the team’s ability to carry it. On rough weeks the margin shrinks. When a long car ride, several nights of poor sleep, a stressful deadline, and an awkward lift stack up, that margin can flip. That flip is what people experience as pain arriving out of the blue.
Three ideas follow from that:
- Sensitivity rises before structure fails. Pain is a protective alarm. Tissues may be irritated long before there is any structural injury.
- Recovery restores capacity. Sleep, nutrition, and stress management raise the “capacity line,” which is why well-recovered people absorb a heavy week without complaint.
- Graded loading is medicine. Thoughtful exposure to movement and strength work teaches tissues to handle more without protest, so ordinary daily tasks stop sitting at the edge of tolerance.
For more focused questions, see common causes of lower back pain, how lower-back symptoms differ and the physical-therapy home exercise program.
What causes lower back pain most of the time?
Potential contributors include muscle or joint sensitivity, disc or nerve-root involvement, changes in activity, sleep and stress. Several factors can coexist, but symptoms alone cannot establish which tissues are responsible or that these six examples account for most cases.
1) Small muscle or tendon strains
A rushed yard-work day, a sudden twist, or picking up a sleepy toddler can irritate the paraspinals, gluteal tendons, or hamstrings. Endurance falls, stiffness rises, and the brain turns the alarm up. It is the classic Monday-morning ache after an ambitious Saturday.
2) Facet joint irritation
Repeated arching or prolonged standing can irritate the small joints at the back of the spine. Bending backward may pinch and bending forward may feel relieving. This pattern shows up often in retail and healthcare workers who spend the day on their feet.
3) Disc-related pain and nerve irritation
Some people develop symptoms after long periods of sitting, bending or travel, particularly when they do not vary positions. That does not prove a disc is injured. Leg pain, altered sensation or weakness should be assessed in context rather than attributed automatically to a sitting posture.
4) Long sitting with few movement breaks
Your back is designed for variety. Fixed postures reduce blood flow and fatigue supportive muscles. That lack of variety is what turns a comfortable morning at a desk into a sore mid-afternoon.
5) Sleep debt and stress
Poor sleep and chronic stress lower your pain threshold and slow recovery. That biochemical context makes it easier for small loads to irritate tissues, which is why flares cluster in the busiest seasons at work.
6) Deconditioning
When glutes and trunk muscles lack endurance, more load shifts to passive structures. That imbalance is a quiet, persistent driver during chores, sport, and even prolonged standing.
Your lower back is a strong, flexible stack of bones, discs, and joints supported by layers of muscles and ligaments. Different problems create different patterns. Recognizing them helps you connect the cause with what you actually feel.
| Source | What it often feels like | Typical triggers | Try this first | See a clinician now if… |
|---|---|---|---|---|
| Muscle strain or spasm | Tight, sore band across the low back | Sudden lift, twist, new workout | Keep walking, gentle heat or ice, short rest, light core work | Fever, trauma, unrelenting night pain |
| Facet joint irritation | Local ache on one side, worse with arching back | Prolonged standing, sway-back posture | Posture reset, hip hinge practice, anti-inflammatory strategies | Pain down both legs or progressive weakness |
| Disc bulge or herniation | Back pain with leg pain below knee, cough or sit worsens | Long sitting, bending, heavy lift | Relative rest from provoking tasks, gentle walking, gradual extension-bias work | Foot drop, bowel or bladder changes |
| Nerve root irritation (sciatica) | Burning or electric pain down leg, numbness | Disc bulge, stenosis | Nerve glide drills, paced walking, avoid end-range flexion early | Progressive numbness or weakness |
| Spinal stenosis | Leg heaviness or pain with walking, relief when leaning forward | Age-related changes | Flexion-bias exercise, walking program with breaks | Sudden, severe weakness or balance loss |
| Sacroiliac or hip referral | Buttock or outer hip pain that mimics back pain | Pregnancy, one-leg-dominant tasks | Glute strength, load sharing, avoid one-leg sag | Inability to bear weight after a fall |
| Osteoporotic wedge fracture | Sudden, localized pain after minor strain in older adult | Low bone density | Medical evaluation, bracing guidance, fall-proofing | Height loss, multiple recent fractures |
Each row points to a different mechanism, which is why one-size-fits-all advice so often disappoints.
Persistent pain is common enough to be worth taking seriously early. National survey data published by the CDC’s National Center for Health Statistics found that 24.3% of U.S. adults had chronic pain and 8.5% had high-impact chronic pain in 2023, with prevalence rising with age. Those figures cover chronic pain of all types, not the back alone, but they are a reasonable argument for dealing with a recurring back problem while it is still an intermittent nuisance.
Nerve-related patterns versus muscle-joint patterns
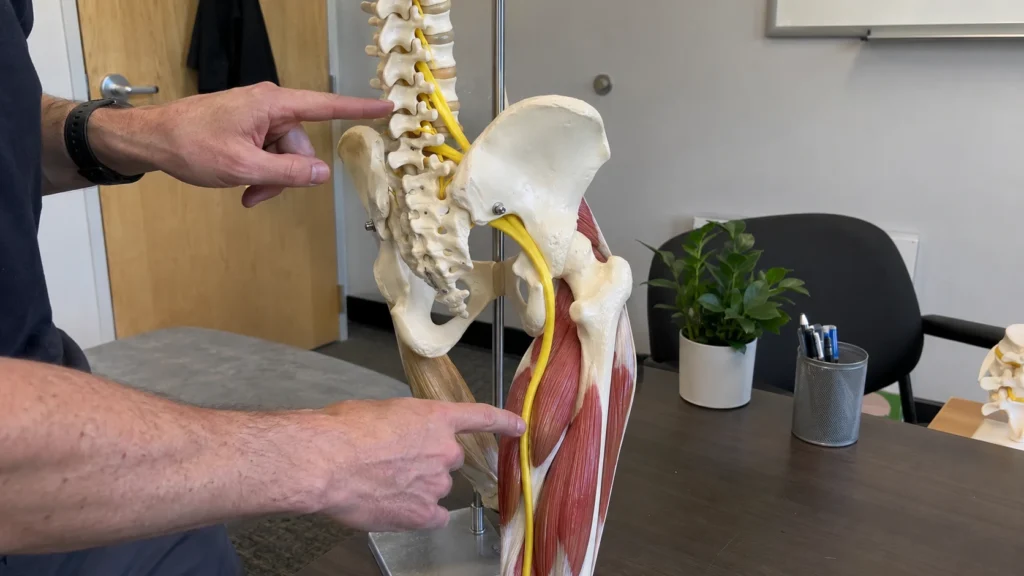
Telling these two families apart changes what you should do next, so it is worth a minute of comparison.
| Pattern | What it feels like | What helps early on | What to watch |
|---|---|---|---|
| Muscle or tendon strain | Achy, stiff, sore on movement, better with gentle motion | Short walking breaks, light heat, easy range-of-motion | Rapid spikes in activity that re-irritate |
| Facet irritation | Pinch with extension, relief with flexion | Hip hinge habits, avoid deep sway-back standing, short trunk endurance work | Standing all day without breaks |
| Disc-related pain ± radicular symptoms | Deeper ache, worse with prolonged sitting, may have leg pain | Frequent position changes, gradual extension bias or neutral spine work | Progressive numbness, weakness, bowel or bladder changes (seek care) |
If your symptoms sit clearly in one row, start with the “what helps early on” column for that row before trying anything more elaborate.
When is lower back pain a sign of something serious?
Get emergency care now for new difficulty passing or controlling urine, loss of bowel control or sensation, or numbness around the genitals or anus. New sciatic pain down both legs or severe or worsening weakness or numbness in both legs also needs emergency care. Get urgent medical assessment for new or worsening weakness in one leg. Get emergency care for back pain after a serious accident. Seek medical advice for fever, a history of cancer or unexplained weight loss.
Seek urgent medical care if back pain is accompanied by any of the following:
- New bowel or bladder trouble
- Progressive weakness, numbness, or tingling in a leg
- Fever, unexplained weight loss, or pain after significant trauma
- Pain that is constant or wakes you at night
None of these mean the worst has happened. They mean the question needs answering quickly rather than over the next few weeks.
Do you really need a scan?
Usually not in the first few weeks. For uncomplicated back pain without red flags, an early X-ray or MRI rarely changes what treatment is recommended, and UK national guidance advises clinicians not to routinely offer imaging in non-specialist settings. Scans become useful when a specific finding would alter the plan — for example, progressive neurological signs or suspected fracture.
There is a second reason to wait. Disc bulges, degenerative changes and mild narrowing are common in people who have no pain at all, so an early scan often produces alarming-sounding words that have nothing to do with why your back hurts this month.
What evidence says about early management

- Keep moving within tolerance. A Cochrane review comparing the two pieces of advice found that people with acute low back pain may get small improvements in pain and function from advice to stay active rather than advice to rest in bed, with little or no difference between the two for sciatica. The effect is modest, but it points the same direction every time.
- Education works. Clear explanations that connect symptoms to load and capacity help people make better choices, which is why flares tend to become shorter once people know how to manage them.
- Graded exercise beats passive care alone. Building endurance and strength raises capacity so daily loads feel lighter.
- Sleep is a treatment multiplier. Recovery amplifies every other input, and it is often the missing piece when back pain keeps returning.
The prevention “priority stack” you can actually follow

Sleep and recovery
Aim for a regular 7 to 9 hours. Keep your wake time consistent, cut caffeine after lunch, and dim screens 60 minutes before bed. Sleep raises tissue tolerance and lowers pain sensitivity, which is why it belongs at the base of the stack rather than as an afterthought.
Movement breaks
Set a gentle timer for every 30 to 45 minutes. Stand, walk to the printer, do five calf raises, or perform three hip hinges. Variety at the spine matters more than any single “correct” position.
👨⚕️ Dr. Arora’s Clinical Note:
A common mistake people make with “movement breaks” is doing them too rarely and too aggressively—then blaming the chair when the back flares again. A more reliable strategy is micro-unloading: tiny, frequent resets that calm disc/joint pressure and re-engage the hip hinge pattern before stiffness “locks in.”
Try the 20–20 reset (2–3 workdays in a row): every ~20 minutes of sitting, stand for 20 seconds and do 3 slow hip hinges (hands on thighs, push hips back, neutral spine) + 2 deep nasal breaths. This often outperforms a single big stretch once an hour.
Quick “direction test” to personalize your break:
- If 5 gentle standing back-bends (hands on hips, small range) makes pain feel more centered or easier, you likely tolerate an extension-bias reset.
- If back-bends feel worse or you get leg heaviness (stenosis-like pattern), use a forward-lean reset instead (hands on desk, slight hip hinge for 10–15 seconds).
The goal is not perfect posture—it’s frequent pressure changes + better loading mechanics so your back stops needing to “shout” by mid-afternoon.
Strength and mobility
Two to three sessions per week are a solid target. Use a mix of:
- Hip hinge work: Romanian deadlift pattern with light dumbbells
- Anti-rotation core work: dead-bugs, suitcase carry
- Glute endurance: bridges or hip thrusts, step-ups
- Mobility “snacks”: cat-camel, open books, hip flexor stretch
Together these raise the ceiling, so ordinary chores and weekend sport stop landing at the edge of your tolerance.
Load management
Increase total training or yard-work load by about 10 to 20 percent per week, not 100 percent in a weekend. Rotate tasks. Do not combine your heaviest lifting day with the longest sitting day if you can help it. These two rules prevent most of the flares that follow a big push.
Work setup that respects your spine
- Chair height: hips slightly higher than knees
- Feet flat or supported
- Screen at eye level
- Keyboard and mouse close so elbows stay near the body
- Option to stand for 10 minutes each hour
A comfortable setup will not immunize you, but it removes a background irritant during long projects.
A 7-day reset plan to calm a flare and build momentum
This plan is for uncomplicated mechanical pain without red flags.
Day 1–2: Calm the system
- Short walks every few hours
- 2 to 3 sessions of easy mobility: pelvic tilts, knee-to-chest, cat-camel
- Light heat for 10 minutes if it feels good
- Skip bed rest; keep moving within tolerance, even if the range is small
Day 3–4: Restore confidence
- Add 2 sets of bodyweight hip hinges and bridges
- 5-minute breathing drill before bed
- Keep the walk habit
- Cap sitting bouts at 45 minutes — the single highest-yield change for desk workers
Day 5–7: Build capacity
- 3 sets of goblet squats with light weight if available
- 3 sets of suitcase carry for 30 seconds per side
- Gentle return to normal tasks with pacing
- End each day with two minutes of spine-friendly mobility
- Expect the improvement to be uneven day to day but clearly upward across the week
What about medications and procedures?
- Over-the-counter options like acetaminophen or nonsteroidal anti-inflammatory drugs can help in short courses for flares.
- Injections and surgeries are reserved for select cases after a period of rehabilitation and only when specific criteria are met. Most people improve without them, which is why education and graded exercise come first.
- Physical therapy helps you identify your drivers, correct movement habits, and progress loading safely. That knowledge is what reduces the chance of the same flare returning.
Putting it all together
- Identify which two or three drivers apply to you specifically.
- Adjust the load this week and rebuild capacity over the next four to eight weeks.
- Watch for red flags and get help promptly if they appear.
- Use a prevention priority stack so wins accumulate even when life is busy.
Why low back pain occurs at different ages
Teens and 20s. Sports overload, deconditioning and long study hours dominate. Technique coaching and basic strength work do most of the job.
30s and 40s. Work sitting and child care lifting add up. The fix is better ergonomics, movement snacks, and consistent walking.
50s and 60s. Stiff hips and spinal arthritis creep in. Recognizing a stenosis pattern — leg heaviness on walking that eases when you lean forward — changes the plan toward flexion-friendly walking.
70s and beyond. Bone health matters more. Gentle strength work and balance training prevent falls and reduce the risk that a small incident becomes a painful fracture.
Programming your week for prevention
Here is a simple template you can adapt once you know which drivers apply in your case.
- Daily: 20 to 30 minutes brisk walking, posture resets each hour you sit
- Twice weekly: Glute bridges or hip thrusts, bird dog, side plank variants, farmer’s carry
- Once weekly: Hip hinge practice with a light kettlebell, suitcase carry, step-ups
- As needed: Short heat or ice, self-massage with a ball, relaxing breath work
Progress slowly. Your goal is consistency, not pain-provoking hero workouts.
When to seek a second opinion
If you have persistent leg symptoms, progressive weakness, or if you are simply not improving after several weeks despite following a good plan, consult a clinician who treats spine conditions regularly. A proper examination and a targeted progression frequently uncover a driver that a generic plan was never going to address.
Conclusion
There is rarely one single villain. For most people, what causes lower back pain comes down to how the spine is moved, loaded and recovered across an ordinary week. The wins are unglamorous and reliable: keep walking, break up long sits, build hip and trunk strength over four to eight weeks, and reserve imaging for the situations where the result would actually change the plan. If symptoms persist beyond a few weeks or any red flag appears, get examined rather than repeating the same routine with more determination.
Related reading: what to do about an unexplained lower-back lump.
Related reading: possible causes of burning in the lower back.
Related reading: what lower-back popping and cracking can mean.
Frequently Asked Questions
Why does my back hurt after long sitting?
Long sitting may aggravate back symptoms because some people become uncomfortable in fixed positions. Changing position or taking a short walk can help, but the response does not identify the precise pain source.
Should I rest completely during a back pain flare?
Prolonged bed rest is generally discouraged for uncomplicated back pain. Try comfortable activity and adjust as symptoms allow, seeking assessment if warning signs develop.
Do I always need an MRI for back pain?
No. Routine MRI is not recommended for uncomplicated back pain. Imaging becomes useful if red flags are present or a finding would alter clinical management.
What are the red flags for back pain?
Seek emergency care for new bladder or bowel dysfunction, numbness around the genitals or anus, severe progressive neurological weakness or major trauma. Back pain with fever or suspected cancer also needs prompt assessment.
Can stress make back pain worse?
Stress and disrupted sleep can increase pain sensitivity or make recovery harder. They are possible contributors, not proof that symptoms are psychological.
Which exercises help the most for back health?
Walking, hip and trunk strengthening or other progressive exercise may help function and recurrence risk. No particular exercise is best for everyone.
How quickly should I increase activity after pain?
Increase activity at a manageable pace guided by comfort, fatigue and next-day function. Fixed percentage increases are not necessary for every patient.
Does posture really matter?
Comfortable posture and changing position regularly may help symptoms. No one sitting or standing posture guarantees protection from back pain.
When is surgery considered for low back pain?
Surgery is considered for select problems, such as major nerve compression or persistent disabling symptoms when specialist assessment shows that an operation is likely to help.
How long do typical back pain flares last?
Many uncomplicated episodes improve over weeks, but recovery varies. Persistent, worsening or unusual symptoms warrant assessment rather than assuming a fixed timeline.
References
- Dahm KT, Brurberg KG, Jamtvedt G, Hagen KB. Advice to rest in bed versus advice to stay active for acute low-back pain and sciatica. Cochrane Database of Systematic Reviews. 2022;(3):CD007612. doi:10.1002/14651858.CD007612.pub2. Cochrane Library
- National Institute for Health and Care Excellence (NICE). Low back pain and sciatica in over 16s: assessment and management. NICE guideline NG59. Published 30 November 2016; last updated 11 December 2020. NICE guideline NG59
- Lucas JW, Sohi I. Chronic pain and high-impact chronic pain in U.S. adults, 2023. NCHS Data Brief, no. 518. Hyattsville, MD: National Center for Health Statistics; November 2024. NCHS Data Brief No. 518



